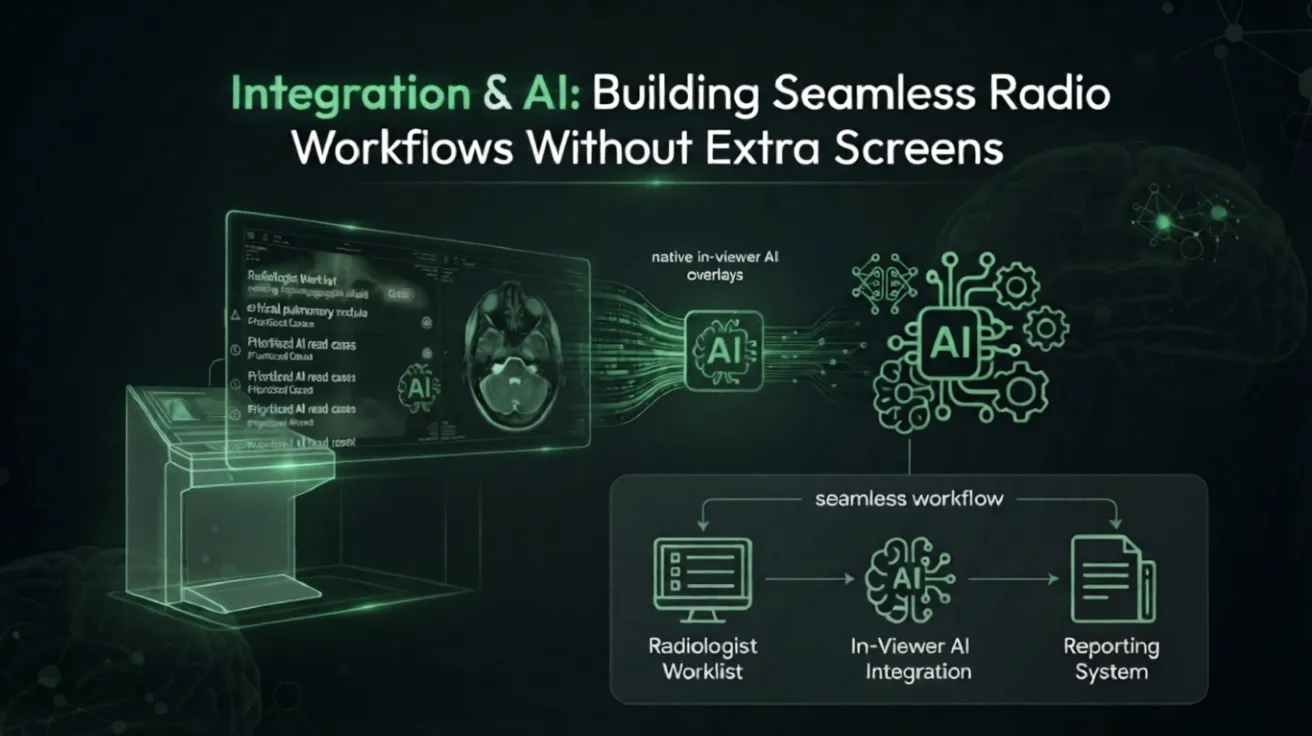
“Agentic AI” has become one of the most overused phrases in healthcare technology marketing. Every vendor now claims an “agent” somewhere in the pipeline. But inside an actual US reporting room in 2026, agentic AI means something far more specific — and far more useful — than a chatbot with a new name.
For radiologists, understanding the real difference between predictive AI and agentic AI in radiology isn’t academic. It determines what these systems can be trusted to do without supervision, and where a radiologist still has to be the final word.
Most AI tools radiologists have used until now are predictive: given an image, they output a finding, a score, or a segmentation. They answer one question and stop. A human takes it from there.
What Agentic AI Actually Does in a Reporting Room Today
Prior-study reconciliation. Instead of a radiologist manually pulling and comparing prior imaging, an agentic workflow can retrieve relevant priors, align measurements across time points, and surface only the meaningful deltas — a nodule that’s grown, a lesion that’s resolved.
Multi-step protocoling. Rather than a single classification (“this needs contrast”), an agentic system can check the ordering context, prior allergy history, and renal function values, then assemble a recommended protocol with the reasoning attached — not just a label.
Draft report assembly, not just structured fields. Predictive AI populates a measurement field. Agentic AI can pull that measurement, the relevant prior comparison, and standard phrasing conventions, then assemble a coherent draft impression section — still requiring radiologist sign-off, but doing far more of the assembly work.
Worklist and communication orchestration. An agentic layer can not only flag a critical finding but also initiate the notification workflow — paging the ordering physician, logging the communication per department policy, and confirming receipt — tasks that today often fall to a technologist or the radiologist themselves.
Where the Guardrails Still Matter
None of this means autonomy without oversight. In US reporting rooms, the diagnostic decision and the final report remain the radiologist’s responsibility — regulatory, legal, and clinical realities aren’t changing in 2026 just because the tooling got more capable.
The meaningful shift is in what the radiologist spends time reviewing. Instead of manually performing the retrieval, comparison, and drafting steps, the radiologist reviews and corrects the agent’s completed work. That’s a fundamentally different cognitive task — closer to editing than authoring — and it changes both the time budget and the skill emphasis of the role.
Radiology groups adopting agentic tools in 2026 are also finding they need new questions for vendors, beyond the usual accuracy benchmarks:
Why 2026 Is the Inflection Point
Two things converged this year that made agentic AI viable in radiology specifically: reporting systems with mature API access that agents can actually act through, and large model reasoning capable enough to handle multi-step clinical tasks without excessive hallucination. Earlier attempts at “autonomous” radiology tools stalled because the underlying models weren’t reliable enough for multi-step chains — one wrong intermediate step compounded into a wrong final output. That reliability gap has narrowed enough in 2026 for cautious, well-scoped agentic deployment, particularly for lower-stakes orchestration tasks like prior retrieval and worklist routing.
What This Means for Radiologists Right Now
Agentic AI in 2026 isn’t replacing diagnostic judgment — it’s absorbing the surrounding administrative and retrieval work that has never required a radiology degree in the first place. For US reporting rooms under sustained volume pressure, that’s a meaningful shift in daily workload, even without touching the diagnostic core of the job.
The groups getting real value aren’t the ones chasing the most autonomous system available. They’re the ones scoping agentic tasks carefully — prior comparison, protocoling support, communication logging — and keeping the diagnostic decision exactly where it belongs: with the radiologist.
Frequently Asked Questions
Curious how agentic AI could fit into your reporting workflow? Contact UEVOLVEAi to learn more.